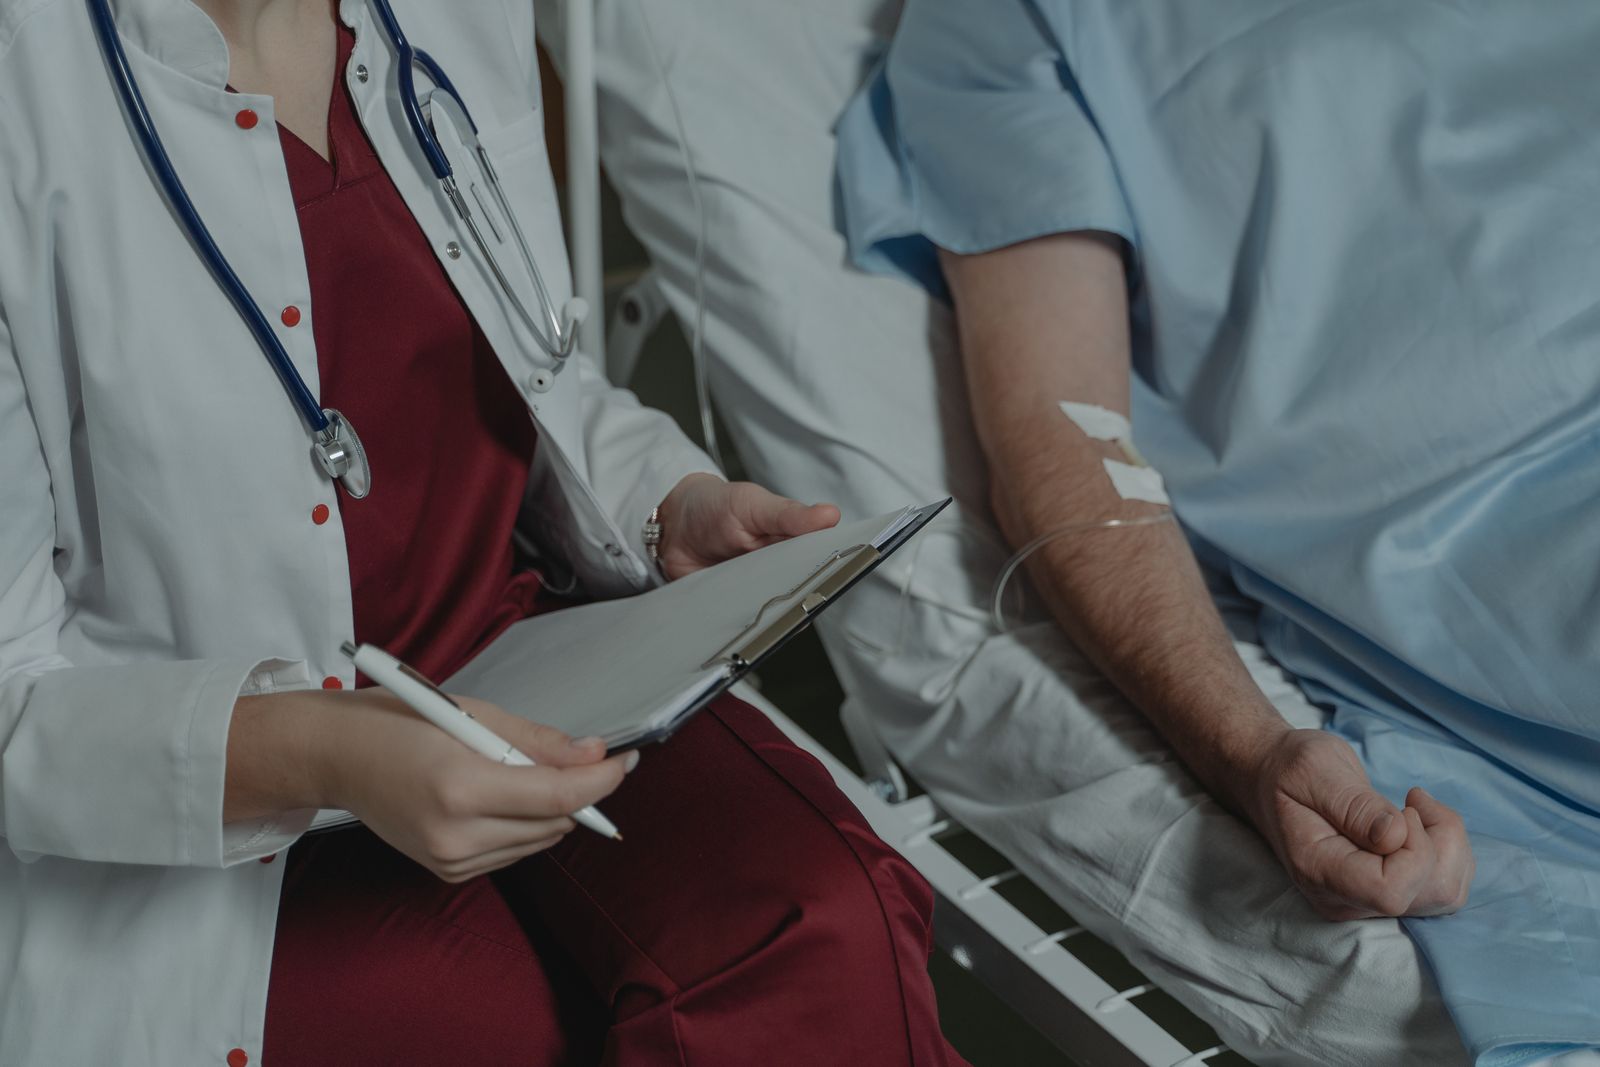
The first hours without alcohol or opioids don’t always reveal how withdrawal will unfold. Someone who initially feels anxious or uncomfortable may face a different situation later, making the choice of care setting more than a question of willpower.
Inpatient medical supervision for alcohol and opioid withdrawal addresses that uncertainty. It isn’t simply waiting for a substance to leave the body. A quality addiction treatment program will monitor how symptoms develop and provide appropriate support as withdrawal progresses.
For individuals and families weighing treatment for themselves or a relative, the distinction between discomfort and medical risk can feel unclear. Understanding how alcohol and opioid withdrawal differ is the starting point for a more informed conversation about care.
The Short Answer: Supervision Keeps Withdrawal Safe
Inpatient supervision matters because it replaces an unsupported, changing situation with repeated assessment and access to treatment. For people at higher risk, that means clinicians are present to recognize complications and respond, rather than waiting for symptoms to become unmistakable at home.
Medically supervised detox means managing the period after substance use stops while clinicians track symptoms, check vital signs, and provide treatment.
Inpatient supervision also allows clinicians to watch for both persistent withdrawal and unwanted medication effects, then adjust care rather than leaving the person to interpret those changes alone. Safe detox is a beginning, not the whole of recovery.
Why Withdrawing Alone Can Turn Dangerous
Alcohol and opioid withdrawal can both be intensely uncomfortable, but their risks aren’t interchangeable. These differences shape what clinicians monitor and why an unsupported attempt to stop can become unsafe.
Alcohol Withdrawal Can Escalate Quickly
Tremors, sweating, anxiety, and nausea can appear early in alcohol withdrawal. More severe symptoms include seizures, hallucinations, and delirium tremens, a serious state involving confusion and physical instability.
Complications can emerge days after the last drink, so an initially manageable period doesn’t establish that the danger has passed.
MedlinePlus explains that alcohol withdrawal can become life-threatening and that moderate-to-severe symptoms may require inpatient treatment, medication, fluids, and close monitoring.
At home, someone may mistake increasing confusion for exhaustion or assume that worsening shaking is something to endure. Clinical assessment distinguishes symptoms that need treatment from those that require urgent escalation.
A history of severe withdrawal also matters, even when current symptoms seem mild.
Opioid Withdrawal Brings Different Dangers
Opioid withdrawal is rarely fatal by itself, but that doesn’t make an unsupported detox safe. Vomiting and diarrhea can cause dehydration, while severe discomfort and cravings can make returning to opioid use feel like the fastest relief.
The period after withdrawal carries another danger: tolerance falls during abstinence. Returning to an amount previously used can therefore cause an overdose. Completing detox doesn’t remove that risk.
Using alcohol and opioids together complicates assessment further. Heart or liver disease and mental health conditions also affect treatment decisions.
Clinicians need the full substance-use and health history, rather than treating every withdrawal episode as the same problem.
What Happens During Inpatient Supervised Withdrawal
Inpatient care follows a cycle of assessment, treatment, and reassessment. An intake evaluation starts the process, but it doesn’t determine every decision that follows.
Continuous Monitoring and Symptom Scoring
Staff reassess symptoms at scheduled intervals around the clock and respond when the person’s condition changes. Treatment staff across inpatient programs describe detox as a series of scheduled checks rather than a single intake assessment.
That distinction matters because symptoms can change after admission.
Monitoring includes pulse, blood pressure, temperature, hydration, and alertness. Clinicians may use CIWA-Ar to assess alcohol withdrawal symptoms and COWS to assess opioid withdrawal.
These scoring tools organize observations and help track changes; they don’t replace clinical judgment or a physical assessment.
Support also includes attention to fluids, food, and rest. For alcohol withdrawal, clinicians commonly provide thiamine to address deficiency risk.
Someone who can’t keep fluids down needs a different response from someone who’s eating, drinking, and remaining medically stable.
Medications Clinicians Commonly Use
Benzodiazepines are commonly used to treat alcohol withdrawal, including reducing the risk of seizures. Clinicians choose treatment according to symptom severity, medical history, and the person’s response.
The goal isn’t simply sedation, but controlled withdrawal with ongoing observation.
For opioid withdrawal, buprenorphine and methadone can relieve symptoms and can also form part of ongoing treatment. Clonidine can address some physical symptoms, but it doesn’t provide the same treatment for opioid dependence.
These medicines aren’t interchangeable, and their selection requires professional assessment. Other substance use, existing medications, alertness, and blood pressure influence the plan.
When an Inpatient Setting Is the Right Call
The appropriate setting depends on medical risk and available support, not on determination. A professional assessment should consider past withdrawal episodes as well as what’s happening now.
Signs a Hospital Stay Is Needed
Hospitals can assess and treat alcohol withdrawal, including complications that require urgent medical attention. Previous withdrawal seizures, delirium tremens, or another severe episode strongly favor a setting with continuous medical supervision.
Heavy or long-term drinking also warrants careful assessment before stopping.
Other reasons for a higher level of care include:
- Use of multiple substances that complicates withdrawal.
- Serious medical illness or unstable psychiatric symptoms.
- Pregnancy, which requires individualized medical planning.
- An unsafe home environment or no reliable support.
Co-occurring conditions need attention alongside withdrawal, rather than being treated as a separate issue to address later. Not every residential program provides hospital-level care, so the assessment should establish what medical capability is needed.
Seizures, confusion, or hallucinations require emergency medical care, not a routine appointment or continued observation at home.
When Outpatient Detox May Be Enough
Inpatient admission isn’t necessary for every withdrawal episode. Outpatient detox can be appropriate when a clinician identifies mild symptoms, low complication risk, reliable home support, and access to regular clinical check-ins.
Outpatient care still means medical oversight. It isn’t the same as stopping alone and hoping symptoms remain manageable.
The plan needs a clear route to reassessment if symptoms worsen or home support breaks down. A doctor should determine whether those safeguards are sufficient.
Mild symptoms at one moment shouldn’t serve as the only reason to rule out inpatient care.
Safe Withdrawal Makes Recovery Possible
Managing withdrawal creates a more stable foundation for ongoing treatment, while continued care addresses needs that don’t disappear when physical symptoms settle.
The starting point is a medical assessment that matches the person’s history, current symptoms, and support needs to the right setting. Withdrawal doesn’t have to be approached as a test of endurance. It deserves a care plan.